The Single Leg Balance Test and What It Predicts About Your Next Twenty Years
Quick Answer: In a study following adults aged 51 to 75, those unable to stand on one leg for 10 seconds had a substantially higher risk of death over the following decade than those who could - and the association held after adjusting for age, sex, body mass, and existing conditions. Balance is not a separate skill from health; it reflects muscle strength, neurological function, vestibular health, and vision working together. It is also highly trainable at any age.
Test it this week, then train it for two minutes a day.


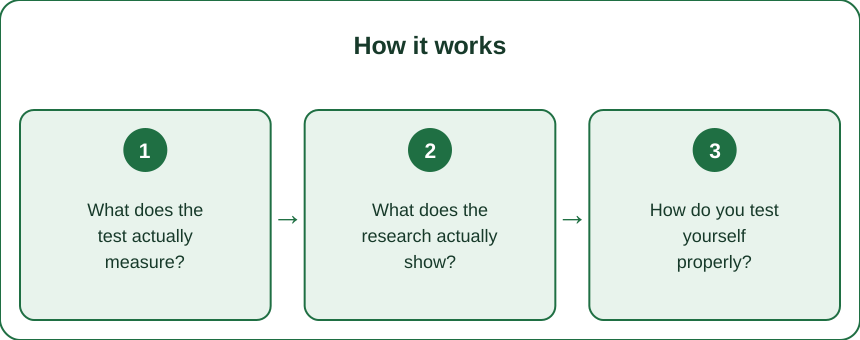
What does the test actually measure?
Far more systems than the word balance suggests.
Standing on one leg looks like a single skill. Physiologically it is an integration task, and it requires at least five systems to work and to communicate:
Muscular strength, particularly in the hip and ankle. The gluteus medius on the standing side prevents the pelvis dropping toward the unsupported leg. The muscles around the ankle make hundreds of tiny corrections per minute. Weakness in either produces visible sway or an immediate failure.
Proprioception. The sense of where your limbs are in space, fed by receptors in muscles, tendons, and joints. This declines with age and with inactivity, and it is one of the first things to deteriorate in a sedentary decade.
Vestibular function. The inner ear system that senses head position and acceleration. Vestibular decline is common with age and frequently goes undiagnosed until someone falls.
Vision. Roughly a third of balance input in a standing task is visual. This is why closing your eyes makes the test dramatically harder, and it is why deteriorating eyesight raises fall risk directly.
Central integration. The brain has to combine those streams fast enough to correct before you tip. This processing speed declines with age and with certain neurological conditions.
Because the test requires all five, failing it is a broad signal rather than a specific one. That is precisely what makes it useful as a screening tool: it does not tell you which system is failing, but it tells you that at least one is, and it does so before a fall does.
There is a second reason it correlates with survival, and it is more direct than the physiological one. Falls are among the leading causes of injury-related death in older adults. A hip fracture at 75 carries a mortality rate over the following year that is genuinely alarming, and the pathway from fracture to decline runs through immobility, muscle loss, and complications. So a balance measure is partly measuring the thing that most often begins that cascade.
What does the research actually show?
A 2022 study published in the British Journal of Sports Medicine followed roughly 1,700 adults aged 51 to 75, who were asked to stand on one leg for 10 seconds without support.
About one in five could not do it. Over a median follow-up of around seven years, those who failed had a notably higher rate of death from any cause than those who passed. The association remained after adjusting for age, sex, body mass index, and pre-existing conditions including heart disease and diabetes.
Some caveats worth stating plainly, because this result gets overstated:
This is an association, not a demonstrated cause. Standing on one leg does not extend life. Being the kind of person who can stand on one leg reflects underlying health that does.
The test is a marker, not a diagnosis. Failing it means something in the chain deserves attention, not that a specific outcome is coming.
Single tests are noisy. Fatigue, footwear, the surface, illness, medication, and how much attention you were paying all affect a single attempt. Test on three separate days before drawing conclusions.
What makes it valuable despite those limits is the combination of properties: it takes ten seconds, requires nothing, is objective, and has a documented association with a hard outcome. Very few health screens have that profile. Grip strength is another, and the two together give a surprisingly informative picture from a couple of minutes of effort.
The practical framing that makes most sense: treat a failed test the way you would treat an unexpectedly high blood pressure reading. Not a verdict, but a specific and actionable prompt to look further and to start doing something about it.
How do you test yourself properly?
The protocol matters, because small variations change the result substantially.
Setup: stand near a wall or sturdy chair, close enough to catch yourself, but do not hold on. Bare feet or thin flat shoes. A hard level floor, not carpet.
Position: place the top of one foot against the back of the opposite calf. Arms at your sides, not out for balance. Look straight ahead at a fixed point.
The test: lift the foot and start timing. Stop when you put the foot down, grab support, move the standing foot, or use your arms to correct.
Do both legs. A meaningful asymmetry - one leg holding twice as long as the other - is worth noting on its own, and often reflects a strength or old-injury difference rather than a systemic one.
Interpretation by age, as a rough guide for eyes open:
- Under 40: 40 seconds or more is typical
- 40 to 49: around 35 seconds
- 50 to 59: around 30 seconds
- 60 to 69: around 20 seconds
- 70 to 79: around 10 to 15 seconds
- Any age, under 10 seconds: worth acting on
The eyes-closed version is much harder and much more revealing, because it removes the visual input that was compensating for everything else. Typical times are dramatically shorter - 10 seconds with eyes closed at 50 is a good result. Only do this with a wall within arm’s reach.
A note on safety: if you are unsteady, have a history of falls, take medication that affects balance, or have a known vestibular or neurological condition, do this with someone present. This is general information, not medical advice, and a persistent balance problem deserves a proper clinical assessment rather than self-testing.

What actually improves balance, and how fast?
It responds quickly, which is the genuinely good news here. Meaningful improvement typically shows within four to six weeks of consistent practice, and the training required is trivially small.
The core principle is specificity plus progressive challenge. Balance improves by practising balance in progressively harder conditions, not as a side effect of other exercise. Strength training helps and does not substitute for it.
A two-minute daily routine, progressed over eight weeks:
Weeks 1 to 2 - baseline. Single leg stand, eyes open, 30 seconds each side, twice daily. Attach it to an existing habit - brushing teeth is the standard suggestion because it takes two minutes and happens twice a day regardless.
Weeks 3 to 4 - remove vision. Single leg stand, eyes closed, near a wall. Start with 10 seconds and build. This is the single biggest step up in difficulty and it targets proprioception and vestibular function directly, because it forces them to work without visual compensation.
Weeks 5 to 6 - add head movement. Single leg, eyes open, slowly turning the head side to side and then up and down. Head movement challenges the vestibular system specifically, and it is what real life demands - most falls happen while doing something, not while standing still.
Weeks 7 to 8 - unstable surface and dual task. Stand on a folded towel or a cushion. Or stand on one leg while counting backwards from 100 by sevens. Dual-task balance - doing something cognitive while balancing - is the most functionally relevant version, because that is the actual scenario in which people fall.
Supporting work that genuinely helps:
- Single-leg strength training - split squats, step-ups, single-leg deadlifts. Two sessions a week. Hip abductor strength in particular is directly protective.
- Ankle strength and mobility - calf raises, and controlled movement through the ankle in all directions
- Tai chi, which has among the strongest evidence bases of any intervention for fall prevention in older adults, and it is enjoyable enough that people continue it
- Yoga, particularly standing balance sequences
- Walking on varied terrain - grass, gravel, trails. Flat pavement asks nothing of the balance system, and a lifetime of it is part of why the system deteriorates.
What does not transfer well: cycling, swimming, and machine-based gym work. All valuable, none of them balance training, because none of them require you to keep an unstable body upright over a small base.
What else should you check if you fail it?
A failed test is a prompt to look at the inputs, and several of them have simple fixes.
Vision, first. Roughly a third of standing balance is visual, and vision changes gradually enough that people do not notice. An eye exam is the single highest-value follow-up to a failed balance test, and it is often the fastest fix. Bifocals and progressive lenses deserve particular mention - they distort the lower visual field, which is exactly where you look when navigating steps, and they are an established fall risk factor.
Medication review. A long list of common medications affect balance - blood pressure medications, sedatives, antihistamines, sleep aids, and some antidepressants among them. Taking several at once compounds the effect. A pharmacist review is free in many places and frequently identifies something adjustable.
Inner ear. Sudden or positional dizziness, particularly when rolling over in bed or looking up, may indicate benign paroxysmal positional vertigo - which is common, frequently undiagnosed, and often resolved in one or two sessions with a specific repositioning manoeuvre. This is worth raising with a clinician because the treatment is quick and effective.
Feet and footwear. Numbness or reduced sensation in the feet degrades the proprioceptive input directly. Diabetic neuropathy is a common cause and needs medical management. Separately, thick-soled cushioned shoes reduce ground feedback - a thinner, firmer sole often improves balance immediately.
Strength, particularly hips. If your balance fails with a visible pelvic drop toward the raised side, that is gluteus medius weakness and it responds well to targeted training.
Vitamin D and B12 status. Both deficiencies are associated with balance problems and falls, both are common, and both are easily tested and corrected. Worth asking about rather than supplementing blindly.
Alcohol. Regular intake affects the cerebellum and vestibular system over time, not just acutely.
The reason to run through this list rather than simply training balance is that training works better when the underlying input problem is also addressed. Practising balance with an uncorrected vision problem is doing the work with one hand tied.
Myth vs Fact: Balance and Aging
Myth: Balance loss is an inevitable part of aging. Fact: Some decline in vestibular and proprioceptive function is age-related. The magnitude of loss most people experience is largely a disuse effect, and it responds to training at every age studied, including in people well into their eighties.
Myth: If you are strong, your balance is fine. Fact: Strength is necessary and not sufficient. Plenty of strong people fail the ten second test, because balance also requires proprioception, vestibular function, vision, and fast central integration. Machine-based strength training in particular develops none of those.
Myth: Balance training needs equipment. Fact: A floor and two minutes is the complete requirement. Wobble boards and balance cushions are useful progressions and entirely optional. The evidence base for tai chi, which needs nothing at all, is stronger than for any device.
Myth: You should not do balance training if you are already unsteady. Fact: That is precisely the group that benefits most, done safely - near a wall, near a chair, ideally with someone present at first. Avoiding it is what allows the decline to continue.
Myth: The ten second test is a definitive health check. Fact: It is one signal with a documented association. It does not diagnose anything, it varies day to day, and it should prompt a look at vision, medication, and strength rather than a conclusion.
Myth: Balance only matters when you are old. Fact: It declines from roughly the fourth decade onward if unchallenged, and the people who reach eighty with good balance are generally the ones who never stopped using it. The training is far easier to maintain than to rebuild.
FAQ: Balance and Longevity Questions, Answered
How often should I test myself?
Every three to six months is plenty. Testing more often mostly measures how you slept. Note both legs and whether your eyes were open, so you are comparing like with like.
Is it worth training if I can already hold 45 seconds?
Yes - move to the harder versions. Eyes closed, head turning, unstable surface, and dual-task. The capacity you want at 75 is built in the decades before it, and standing still on two feet does nothing to maintain it.
Does yoga count as balance training?
Standing balance postures absolutely do, and they progress naturally. Flow sequences that never hold a single-leg position for long are less effective for this specific purpose. Tai chi has the strongest fall-prevention evidence of the movement practices.
Can medication really affect this much?
Yes, and it is one of the most commonly missed factors. Sedatives, some blood pressure medications, antihistamines, and combinations of several drugs all contribute. Never stop a medication on your own - ask for a review.
Should I worry if one leg is much worse than the other?
A modest difference is normal and usually reflects your dominant side or an old injury. A large asymmetry, or one that appeared suddenly, deserves a clinical opinion rather than a training plan.
How long until I see improvement?
Most people notice a meaningful change within four to six weeks of daily practice, and the first two weeks often produce the fastest gains because much of the early improvement is neurological rather than structural.
TL;DR:
- In a study of adults 51 to 75, inability to stand on one leg for 10 seconds was associated with substantially higher all-cause mortality over the following years, independent of age and existing conditions.
- The test integrates strength, proprioception, vestibular function, vision, and central processing - which is why failing it is a broad signal.
- Test properly: bare feet, hard floor, arms down, both legs, on three separate days. Under 10 seconds at any age warrants attention.
- Balance responds fast. Two minutes daily, progressed from eyes open to eyes closed to head movement to dual task, produces change in four to six weeks.
- If you fail, check vision, medication, inner ear, foot sensation, and hip strength before assuming it is just age.
It costs ten seconds. Very little else in health screening has that ratio of information to effort.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
